

MUSE Cells vs Mesenchymal Stem Cells (MSCs) Guide
Why do so many people assume the newest cell type is automatically the better one, even when the clinical evidence hasn't caught up yet? In regenerative medicine, that question matters because MUSE cells vs Mesenchymal Stem Cells (MSCs) is not a contest between “old” and “new,” it's a comparison between a well-studied stromal therapy and a rare, more recently defined subpopulation with intriguing early signals.
| Feature | Mesenchymal Stem Cells (MSCs) | MUSE Cells |
|---|---|---|
| Biological role | Broad stromal/mesenchymal population with signaling and tissue-support effects | SSEA-3-positive subpopulation found within MSC cultures |
| Research history | Long-established field, with roots that trace back decades | First reported in 2010 as a distinct stress-enduring subpopulation |
| Differentiation profile | Multilineage mesenchymal potential | Pluripotent-like behavior across all three germ layers in early research |
| Clinical maturity | Much larger human evidence base | Promising, but still developing in human studies |
| Practical use | Commonly chosen when the goal is immune modulation and tissue support | Considered when the question is targeted neurological research or a newer precision strategy |
Understanding the Cellular Frontier
The practical question is not whether a cell type is newer. It is whether the cell has enough human data, a clear manufacturing identity, and a plausible fit for the condition being treated. MSCs and MUSE cells answer those questions very differently.
Two related but not interchangeable cell populations
Mesenchymal stem cells are the broader category. Classic MSCs are defined by the International Society for Cellular Therapy through plastic adherence, a specific immunophenotype, and multilineage differentiation potential, with published reviews noting differentiation toward bone, cartilage, adipose, tendon, and muscle (MSC definition and lineage criteria). Clinically, that makes MSCs useful as signaling cells, not as a direct source of full tissue replacement.
MUSE cells, short for multilineage-differentiating stress-enduring cells, are a distinct subpopulation within mesenchymal cultures. They were identified as SSEA-3-positive cells, and their defining feature is a stress-resistant biology that separates them from the bulk MSC population (MUSE cell rarity and marker profile). That is why they draw attention, but attention is not the same as superiority.
A more specialized cell type is only an advantage when the clinical question requires that specialization.
That distinction matters in day-to-day decision-making. MSCs remain the more established option for broad regenerative programs, especially in orthopedic and systemic care, while MUSE cells are still being watched for their unusual biology in nervous system research. For readers who want a clearer explanation of lineage potential, our multipotent vs pluripotent stem cells resource is the right place to start.
Decades of Research vs Emerging Science

MSC science has an unusually long runway. The term was formally coined by Arnold Caplan in 1991, but the research lineage reaches back to the 1960s and earlier, including foundational bone-marrow work by Friedenstein and colleagues showing clonogenic cells that could generate bone and reticular tissue after transplantation (historical MSC lineage and early bone-marrow studies). That history is why MSCs sit at the center of most clinical conversations today.
Why the age of the evidence matters
A long research history does not make a therapy perfect, but it changes how clinicians think about risk, manufacturing, and expectations. MSCs have had decades to move from laboratory observation into translational medicine, which is why they often serve as the reference point when newer cell types are discussed. For a deeper look at the MSC evidence base, see our mesenchymal stem cell research overview. MUSE cells were first reported in 2010 by Dezawa's team in Japan as a stress-enduring subpopulation inside mesenchymal tissues.
That difference matters. MUSE cells should be understood as a newer concept inside an older MSC field, not as a separate lineage with six decades of independent validation. Their case is still being built from biology, injury response, and early human studies.
How MUSE cells differ from embryonic and induced pluripotent stem cells
MUSE cells are often described as pluripotent-like, but they are not embryonic stem cells and they are not induced pluripotent stem cells. Early research found lower proliferative activity and no teratoma formation in the reported transplant settings, which is one reason they have drawn attention as a potentially safer pluripotent-like population (pluripotent-like behavior and non-tumorigenic profile). That does not prove clinical superiority, but it does give them a clearer safety profile than many newer cell concepts.
For clinicians, the practical takeaway is straightforward. MSCs remain the mature platform with the deeper evidence base and the broader real-world use, especially in orthopedic and systemic care. MUSE cells are the more intriguing frontier, particularly for nervous system questions where unique biology may matter.
Neurological Research and Clinical Signals
Neurology is where MUSE cells have drawn the most serious attention. That interest comes from early human data that are small, but still organized enough to be more credible than the usual anecdotes that surround emerging regenerative therapies. The honest reading is simple, the signal is promising, not proven.
What the Stroke Trial Showed
The most important trial was a randomized, placebo-controlled study in subacute ischemic stroke. It enrolled 25 treated patients and 10 placebo patients, and 40% of treated patients met the study's functional response threshold at 12 weeks, compared with 10% of placebo patients (controlled stroke trial of CL2020). That is an early signal worth taking seriously.
The same publication also shows the limits of the evidence. The sample was small, and the treatment was a specific intravenous protocol, not proof that every MUSE preparation will behave the same way. It supports interest in one carefully studied product in a narrow stroke population, while leaving broader use unresolved.
Clinical takeaway: an early positive signal is not the same thing as a standard of care.
The Spinal Cord Injury Study, and Why It Still Matters
A separate 10-person cervical spinal cord injury study reported improvement, but it had no control group. That limitation matters, because uncontrolled neurologic studies can look better than they are when spontaneous recovery is part of the natural course.
Even with that caveat, the study still matters. It shows that MUSE cell-based products are being tested in central nervous system injury with clinical follow-up, and the early safety signals help explain why the field continues to move. The findings do not justify treating every neurological diagnosis the same way, and they do not let us generalize from one intravenous protocol to all future preparations.
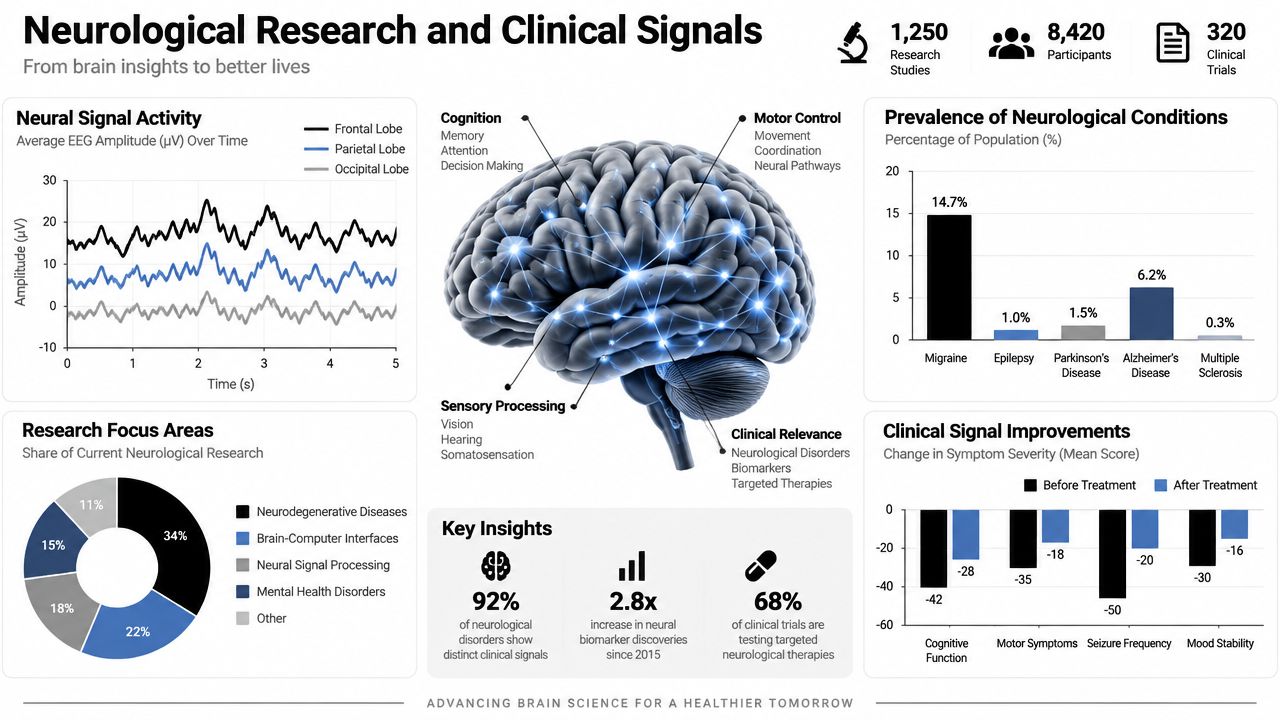
The practical point is straightforward. MUSE cells for neurological research are the strongest part of the story so far. That does not make them a routine recommendation for every neurological condition. It does mean they deserve consideration, especially for brain and spinal cord injury questions. For patients exploring broader neurologic support options, the regenerative neurology resource provides a useful clinical overview.
Are MUSE Cells Better for Joints
No human research has shown that MUSE cells outperform MSCs for orthopedic injections. That is the answer patients usually want first, and it's the one that matters most clinically. Laboratory and animal findings are interesting, but they don't establish a real-world advantage for knees, shoulders, hips, or spine.
Why orthopedics still favors the broader MSC evidence base
Orthopedic care is where the larger MSC literature still carries the day. MSCs have a much broader record in musculoskeletal settings, and their signaling and immune-modulating effects match what clinicians usually want in joint disease. That's one reason I wouldn't automatically recommend the newer, more expensive cell option just because it sounds more advanced.
MUSE cells may be biologically fascinating, but MUSE cells for joint injections are not proven to deliver better outcomes than standard MSC approaches. In the absence of human superiority data, the wiser choice is often the therapy with the deeper evidence base, the clearer clinical rationale, and the simpler interpretation of expected benefits.
| Clinical Evidence Comparison | Mesenchymal Stem Cells (MSCs) | MUSE Cells |
|---|---|---|
| Human orthopedic evidence | Broad and mature | Limited |
| Human neurologic evidence | Expanding, but indirect for this question | Early and still developing |
| Head-to-head superiority in joints | Not established against MUSE cells | Not established against MSCs |
| Typical clinical framing | Signal modulation, immune support, tissue support | Precision subset with early pluripotent-like interest |
| Practical recommendation for joints | Often the default evidence-based option | Considered selectively, not automatically |
At Longevity Medical Institute, that means the newer option is not the automatic default for a joint issue. If a patient wants a MUSE-enriched strategy after an informed discussion, it can be made available, but the conversation starts with what the evidence supports. More detail on our joint-focused approach is available in the stem cell treatment for joints resource.
Inside the LMI Biotechnology Lab
Cell therapy should never feel like a black box. A serious program makes the lab work, physician oversight, and reporting line up, because patients deserve to know what was prepared and what was documented.
What gets verified before treatment
At LMI, MSCs and MUSE-enriched preparations are prepared fresh for physician-supervised treatment. The key lab document is the flow cytometry report, which verifies the relevant cell-marker profile for the preparation. That verification confirms the product's cellular characteristics and helps show whether the material matches the intended preparation.
It does not tell us how one individual patient will respond. That distinction matters. Flow cytometry is a quality and identity tool, not an outcome predictor.
Practical rule: a valid marker report confirms cellular characteristics, it does not promise a clinical result.
What transparency should look like
A patient should never be left guessing about whether a product matches the published trial material. Manufacturing differences matter, and they should be stated plainly rather than blurred by marketing language.
A proper workflow should answer three questions clearly:
What was prepared? The report should identify the cell population and its marker profile.
What was verified? The data should show the relevant identity markers, and when applicable, other quality measures documented in the report.
What does it mean? The report supports characterization, not certainty about a personal outcome.
That transparency is one reason we treat the lab as part of the consultation, not a separate technical footnote. For readers who want the manufacturing philosophy behind that approach, the why in-house biotechnology and fresh stem cells matter resource gives the clearest overview.
Making the Right Treatment Selection
The right choice is rarely the newest product or the highest price. It comes down to the tissue problem, the biologic rationale, and the strength of the human evidence. In practical terms, MSCs remain the default reference for many musculoskeletal and broader regenerative uses because the clinical record is much larger.
How the decision is usually made
The condition should drive the decision, not the label. For joints, systemic inflammation, and many recovery-oriented programs, MSCs still make the most practical sense because the evidence base is larger and the therapeutic argument is easier to defend. For neurological questions, MUSE cells are the more interesting frontier, but they remain an emerging human therapy.
Longevity Medical Institute works with five allogeneic stem cell types, including placental, Wharton's jelly, adipose, endometrial, and dental pulp. That range matters because no single cell source fits every patient or every indication. A careful evaluation should compare the biologic target, the expected mechanism, and the available clinical data before anyone selects a product.
A clinician's rule for choosing well
Use the simplest cell strategy that fits the clinical problem and the evidence. If the goal is orthopedic support, MSCs usually remain the standard reference. If the question is whether a MUSE-specific approach makes sense for a neurologic concern, that is a narrower discussion, and it should stay tied to current human data rather than marketing claims.
Restraint usually serves patients better than enthusiasm. A careful physician evaluation, a review of the actual data, and a clear discussion of what is known versus what is still experimental will usually lead to a better decision than chasing the newest label.
Frequently Asked Questions
Are MUSE cells a type of MSC?
Yes. MUSE cells are a subpopulation found within MSC cultures, not a separate adult cell lineage. That is why they are discussed as a more specific subset, not a replacement for MSCs.
What has been studied in stroke?
The main human signal so far comes from a small randomized, placebo-controlled trial in subacute ischemic stroke. The result was promising enough to justify interest, but not strong enough to change standard practice. Before this approach can be treated as routine care, a confirmatory trial would need to show the same direction of benefit in a larger group, with clearer patient selection, durable follow-up, and enough consistency to rule out a chance finding.
Why don't MUSE cells form teratomas in the animal studies?
Early research describes MUSE cells as pluripotent-like with lower proliferative activity and no teratoma formation in reported transplant settings. That does not make them risk-free. It does place them in a different safety discussion from embryonic stem cells and induced pluripotent stem cells, which carry a different tumor-risk profile.
Are MUSE cells proven better for joint injections?
No. There is no human evidence showing that MUSE cells outperform MSCs for orthopedic injections. For joints, MSCs still carry the larger evidence base and the more defensible clinical case.
How does LMI verify its cell preparations?
Through flow cytometry reports that document the relevant marker profile, including the SSEA-3-positive population for MUSE-enriched preparations. That kind of verification tells you what is in the product. It does not tell you how an individual patient will respond.
MSC therapy remains an important part of our regenerative programs, and MUSE cells remain an interesting direction in neurological research. If you want a physician-led discussion about whether MSCs or a MUSE-enriched strategy fits your goals, visit Longevity Medical Institute and schedule a consultation. We will review the evidence, your diagnosis, and the practical trade-offs with the kind of clarity patients deserve.
Author
Dr. Kirk Sanford, DC, Founder & CEO, Longevity Medical Institute. Dr. Sanford focuses on patient education in regenerative and longevity medicine, translating complex therapies into clear, practical guidance for patients.
Medical Review
Dr. Félix Porras, MD, Medical Director, Longevity Medical Institute. Dr. Porras provides clinical oversight and medical review to help ensure accuracy, safety context, and alignment with current standards of care.
Last Reviewed: September 29, 2026
Short Disclaimer
This information is for educational purposes only and isn't medical advice. It doesn't replace an evaluation by a qualified healthcare professional. For personalized guidance, please schedule a consultation.